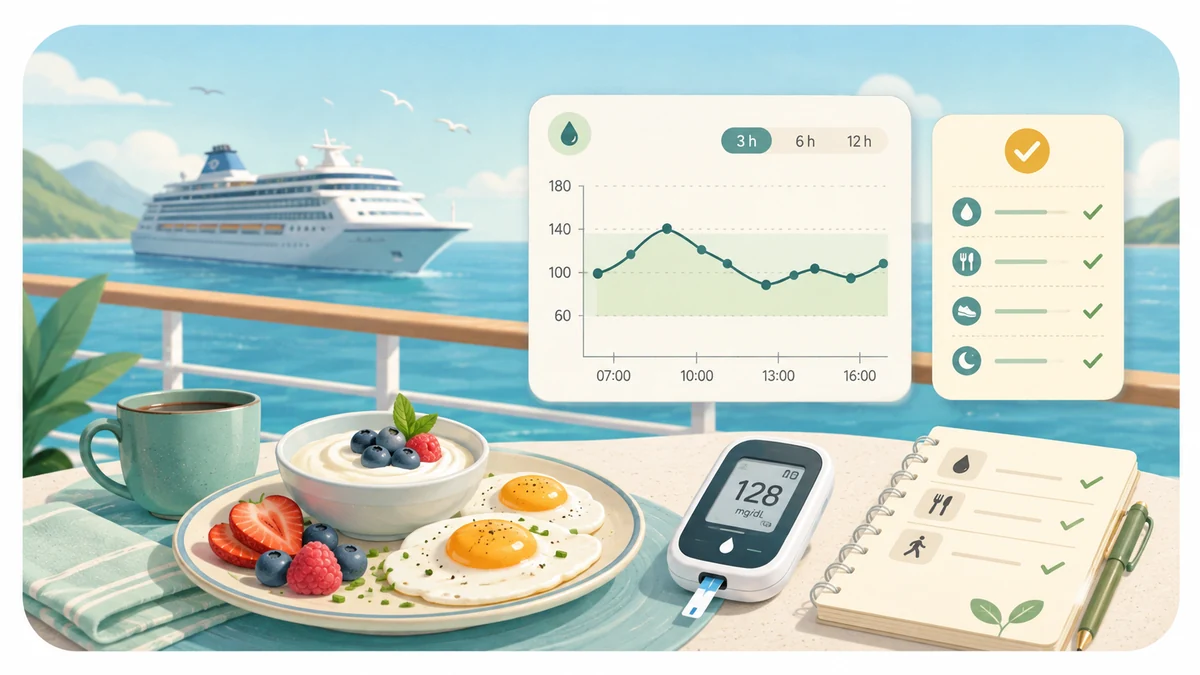
1) What are the key questions before the trip?
Many problems can be avoided if you clarify a few things beforehand: ideally directly with the cruise line (e.g. TUI Mein Schiff or AIDA):
- Is there a nutrition/allergy consultation on board you can join?
- How is diabetes handled (e.g. labelling, advice, special requests)?
- Is there a ship’s doctor who can help in an emergency (e.g. with hypoglycaemia, giving glucose)?
- What options are there if you need to adjust food (e.g. no sugar / no flour / low carb)?
I haven’t taken part in such consultations so far, so this is mainly a pragmatic field report.
2) Drinks: the fastest lever for stable values
Non-alcoholic drinks. On Mein Schiff and AIDA you typically get: water (still/sparkling), Coke Zero / Light (depending on the system) and various teas (e.g. green tea).
Alcoholic drinks. Here what counts most is: carbs per 100 ml, and they add up.
- Beer: very variable by type. Example: Bitburger about 3.1 g carbs / 100 ml → 330 ml ≈ 8.25 g carbs. Example: Desperados about 5.5 g carbs / 100 ml → 330 ml ≈ 18.15 g carbs.
- Cuba Libre “Zero”: white rum + lime + Coke Zero → for me usually barely a rise.
- Moscow Mule: vodka + lime + ginger beer → ginger beer is often sugary, so check the carbs.
3) Postmix from the tap: “Did I really get Zero?”
On some ships, bar drinks often come from a dispenser: same tap, different button: cola, Coke Zero, water etc. That regularly made me wonder: was it really Zero?
My solution: a refractometer / sugar meter, of the kind used e.g. to measure sugar in grape must. It isn’t perfect, but it reliably shows the tendency: sweet or rather “Zero”. The trick of testing drinks with a classic blood glucose meter didn’t work for me, because the device expects blood. That may differ by manufacturer.
Practical rule: trust your senses. If it tastes different, it probably is. But a simple tendency check takes a lot of the stress out. On Mein Schiff I mainly had this issue at bars. In restaurants with self-service stations it’s easier, because you control the source yourself.
4) Food on board: orientation without perfect labelling
At buffet restaurants, dishes often aren’t labelled well enough to estimate carbs precisely. So a pragmatic approach helps:
- Sauces are often the “hidden” carb source (flour/thickening/sugar).
- Rule of thumb: the more “creamy” and thickened, the more likely extra carbs.
- I often chose meat/fish: ideally without sauce or with only a little.
That makes the decision easier and reduces “surprises”.
5) Breakfast: ideal for stabilising the day
I found breakfast particularly strong on AIDA and Mein Schiff, because you can eat very blood-sugar-friendly there: omelette, scrambled eggs, fried egg, maybe sausages (blood-sugar-friendly, but not ideal daily for other health goals), with black coffee or green tea. A protein-rich breakfast helps me keep the morning more stable, especially when blood sugar tends to rise after getting up.
6) When I’ve “sinned”: compensating without drama
Honestly: eating “perfectly” all the time is no fun. Sometimes it’s mashed potato, pasta or an ice cream: that’s part of a holiday. What works well for me: movement to compensate (e.g. the gym on board).
7–9) Timing, measuring & my routine
I measure about one hour after eating to catch my personal peak, and find the individual timing through a simple log. Not every value needs a perfect explanation, what matters is the long-term trend and regular medical check-ups.
10) Mein Schiff 3: a quick impression
The cabins were strikingly clean and cleaned twice a day for us. The staff were friendly. A small tip often lifts the mood further. The entertainment seems modest at first but becomes much livelier: especially on sea days. Overall I found the atmosphere very pleasant.
11) Relaxation: underrated, but decisive
The most important point on a cruise for me is: lower the stress. On shore excursions you quickly stress yourself unnecessarily. You don’t have to be part of everything. Relaxation lowers the stress level and thus often the blood sugar too. Under stress I sometimes see +20 to +30 mg/dl, without food. That makes sense: the body provides energy (stress response). If you fight it internally, you amplify the effect. For me: less stress, more light movement, more rest – that often stabilises more than “perfect” food.
12) Training: helpful, but not as a stress trap
Training should be fun. You notice overexertion quickly. What impresses me every time: how fast blood sugar can fall during training. Example (for me): start at 115 mg/dl, after eating up to 160 mg/dl (rising), training (bike/running) → can quickly fall to ~70 mg/dl, then often settles back around 120–130 mg/dl.
The body has a “comfort level” it wants to return to. That also applies with higher fasting values. If I’m at 140–150 mg/dl fasting, I often end up back there after training. Reasons can be stress, infection, poor sleep, mental strain. Not every peak has a clean explanation. What matters is the long-term development and regular medical check-ups.
13) Shore days: a chance for stable values
Shore days are often ideal because you walk a lot. If I plan a long walking shore day, I sometimes eat a bit “more” beforehand, e.g. 2 rolls with cheese plus egg. Protein and fat slow the rise for me, and the movement burns off the rest. With guided tours involving a lot of bus travel it’s different: then I prefer a protein-rich, lower-carb breakfast, because on the bus you can barely counteract if you get symptoms.
Key takeaways
- Drinks are the fastest lever: water, Coke Zero, tea – avoid postmix and sweet cocktails.
- At the buffet, keep an eye on sauces; a protein-rich breakfast stabilises the day.
- Easy movement after eating often works more lastingly than hard training.
- Lower the stress: relaxation stabilises me more than “perfect” food.
- Measure one hour after eating – find your individual timing via a log.
The original measurement record remains unchanged. This section adds only method, sources, limitations and a reproducible follow-up plan.
The central question in this article
The article “Blood sugar on a cruise: my hands-on field report” examines how travel routines, buffets, drinks, heat, activity and sleep can be combined into a practical overall plan. The quality test is not whether one curve creates a compelling story. It is whether the timeline, data source, surrounding circumstances and alternative explanations are documented well enough for readers to separate observation from interpretation.
What the data show — and what they do not
A personal series can show timing and recurring patterns. It cannot by itself prove which physiological mechanism caused the pattern. Direct observation, plausible explanation and open question are therefore separated. Numbers remain linked to unit, time and data source, and missing details are not replaced with guesses.
Reading CGM correctly
Continuous glucose monitoring measures interstitial glucose. During rapid rises or falls, the display may follow blood glucose with a delay. Pressure on the sensor, a newly inserted sensor, hydration and short data gaps can add uncertainty. When a reading does not match symptoms or the situation, a confirmatory measurement may be appropriate depending on the clinical significance.
Technical context: Cruise travel and daily routines
A cruise combines buffets, postmix drinks, alcohol, heat, activity, shifted sleep and unfamiliar schedules. A simple plan is therefore more useful than trying to predict every meal perfectly. At a buffet, a fixed sequence creates orientation: scan first, choose one planned portion, then decide deliberately whether more is needed. Sauces, pastries, sweet drinks and large mixed portions remain common uncertainties.
Article-specific interpretation
For “Blood sugar on a cruise: my hands-on field report”, this means first establishing which of the four phases — Plan before travel, Check sources on board, Link meals and movement, Emergency and return plan — are actually documented. A missing phase is not guessed from the curve. This matters especially because how travel routines, buffets, drinks, heat, activity and sleep can be combined into a practical overall plan. More decimal places do not improve research; more complete context does.
Alternative explanations
The competing influences considered are Buffet and portions, Postmix and alcohol, Heat and hydration, Sleep and shore days. Several can act at once and partly mask one another. No factor is therefore declared causal merely because it occurred close in time. A plausible explanation remains labelled as plausible until a targeted comparison supports it.
Data sheet and provenance
The data sheet for “Blood sugar on a cruise: my hands-on field report” records more than the start and peak. It also covers Plan before travel, Check sources on board, Link meals and movement and Emergency and return plan. Each section states whether a value was measured directly, read from a screenshot, calculated from raw data or reconstructed from memory. This keeps strong research separate from details that require later verification.
Typical failure modes
Common failure modes in this topic are incomplete portions, an incorrect time origin, events added retrospectively and observation ending too soon. For “Blood sugar on a cruise: my hands-on field report”, Buffet and portions and Heat and hydration are particularly important competing explanations. A finding is therefore given more weight only when the same direction appears on several sufficiently similar days and counterexamples are documented as well.
Editorial decision
The editorial decision is to keep the personal experience visible without turning it into universal advice. Headline, hero image, alternative text, captions and conclusion must communicate the same uncertainty. When the article contains an open question, it ends with the next testable step — Pack essential equipment — rather than a claim of effect.
Interpretation matrix
The interpretation matrix for “Blood sugar on a cruise: my hands-on field report” assigns every core statement to one of four classes: directly measured, calculated from several readings, physiologically plausible or still open. Direct measurement does not automatically establish causation. A calculated result requires a documented formula and time window. Plausible means consistent with physiology and timing but not isolated in the personal data. Open means that data, repetitions or comparison conditions are missing.
Publication review
Before publication, a final review asks whether the hero image matches the actual message of “Blood sugar on a cruise: my hands-on field report”, whether every number can be found in the text, whether units and timing are correct, and whether every image has alternative text and a caption. It also checks that Buffet and portions or Postmix and alcohol has not accidentally been turned into a proven cause. Only then is the article editorially complete.
Reproducible follow-up plan
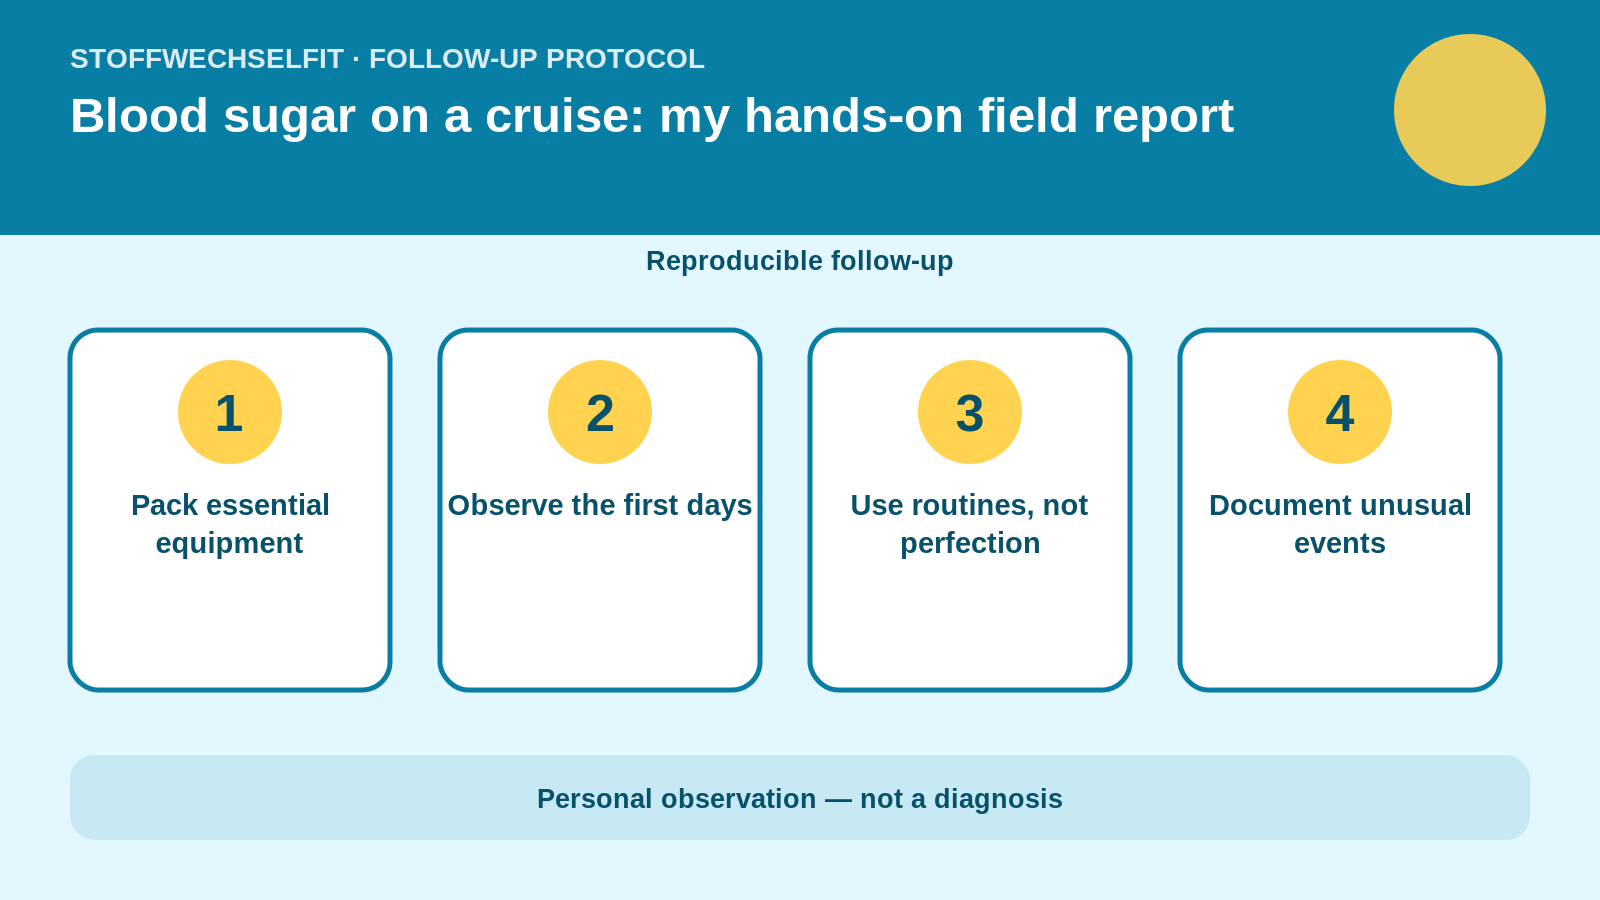
The next useful comparison follows four steps: Pack essential equipment, Observe the first days, Use routines, not perfection, Document unusual events. This sequence turns a spontaneous observation into a protocol and reduces the risk of selecting only spectacular days while forgetting ordinary patterns.
What can be transferred
The transferable lesson from “Blood sugar on a cruise: my hands-on field report” is therefore not necessarily the exact number. What transfers are the question, the documented conditions and the handling of uncertainty. Other people may respond very differently because of treatment, fitness, insulin sensitivity, digestion or comorbidity.
Comparison rather than snapshot
A credible comparison starts with one clear question and conditions that are as similar as possible. Starting value, trend, time, portion, drinks, activity, sleep, stress and medication all belong in the record. Not every factor can be controlled; the important point is to show differences rather than explain them away afterwards.
State the observation window
Thirty minutes answers a different question from two, four or twelve hours. The article therefore states when observation begins and recognises that mixed meals, alcohol or intense activity can act later. A peak is not interpreted without the pattern before and after it.
Personal readings are not universal limits
Typical guideline targets can provide orientation but require individualisation. Age, comorbidities, pregnancy, medication, hypoglycaemia risk and personal treatment goals change the interpretation. The self-observations shown here do not replace diagnosis or treatment decisions.
Practical safety framework
Marked symptoms, recurrent hypoglycaemia, very high readings, ketones or a pattern that does not fit the situation require clinical assessment rather than another self-experiment. People using insulin or glucose-lowering medication must not derive dose changes or corrections from a blog post.
Further technical limitations
At bars, the source matters. Self-service, sealed bottles or visible cans are easier to verify than an unknown postmix. With alcohol, amount, food, hydration and individual treatment all matter. Movement on board and during shore excursions can be useful, but it is not compulsory compensation. Footwear, heat, hypoglycaemia risk, medication and general fitness determine what is safe.
Questions before drawing a conclusion
- Is the starting value for “Blood sugar on a cruise: my hands-on field report” documented with trend and time?
- Are Buffet and portions and Postmix and alcohol described adequately?
- Did observation continue through “Emergency and return plan”?
- Is there a comparison day after “Pack essential equipment”?
- Is each statement clearly labelled as personal, plausible or generally established?
Sources and context
- American Diabetes Association: Standards of Care in Diabetes—2026, health behaviours and exercise
- American Diabetes Association: Standards of Care in Diabetes—2026, glycaemic goals
- NIDDK: Healthy Living with Diabetes
- WHO: Healthy diet
- EFSA: Sweeteners – current re-evaluations and safety assessments
Medical notice: This article explains a personal observation and general context. It does not replace diagnosis, treatment adjustment or emergency care.