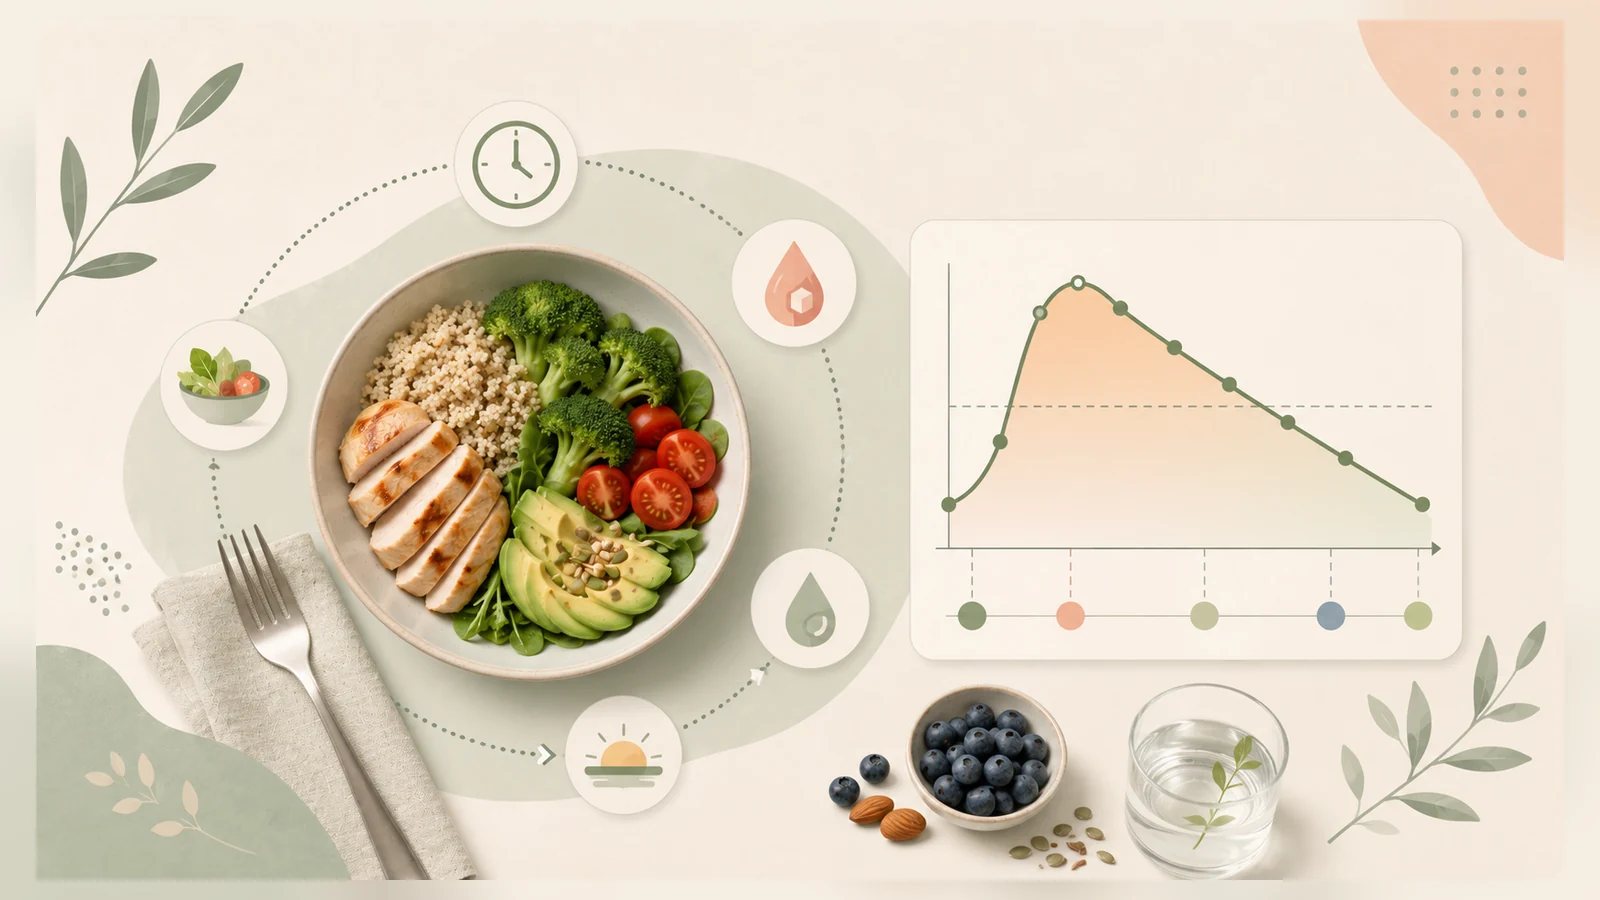
Blood sugar after eating is medically called “postprandial”. It’s a sensitive early indicator: it often shows abnormalities before the fasting value goes out of range.
Which values apply
In people without diabetes, blood sugar two hours after eating is usually below 140 mg/dl (7.8 mmol/l) and then returns to baseline.1 For people with diabetes, the ADA gives a general target of below 180 mg/dl one to two hours after the start of the meal.2
What determines the height of the spike
The most important factor is the amount of carbohydrate in the meal.1 But composition matters too: fibre, protein and fat slow absorption and dampen the spike. Further influences are sleep, stress and individual carbohydrate tolerance.1
Why repeated high spikes are unfavourable
Occasional peaks are normal. Frequent, pronounced postprandial spikes, however, are considered an independent risk factor for cardiovascular disease and contribute to downstream damage via oxidative stress.3 So it’s worth looking not only at the fasting value and HbA1c, but also at what happens after meals.
Key takeaways
- Without diabetes: usually below 140 mg/dl two hours after eating.
- ADA target in diabetes: below 180 mg/dl (1–2 hours after eating).
- Carbohydrate amount most strongly determines the height of the spike.
- Fibre, protein and movement dampen the spike.
- Repeatedly high spikes are an independent risk factor.
The original measurement record remains unchanged. This section adds only method, sources, limitations and a reproducible follow-up plan.
The central question in this article
The article “Blood sugar after eating: what is normal and what drives the spike” examines how starting value, timing, height, duration and return of a post-meal curve are evaluated together. The quality test is not whether one curve creates a compelling story. It is whether the timeline, data source, surrounding circumstances and alternative explanations are documented well enough for readers to separate observation from interpretation.
What the data show — and what they do not
A personal series can show timing and recurring patterns. It cannot by itself prove which physiological mechanism caused the pattern. Direct observation, plausible explanation and open question are therefore separated. Numbers remain linked to unit, time and data source, and missing details are not replaced with guesses.
Reading CGM correctly
Continuous glucose monitoring measures interstitial glucose. During rapid rises or falls, the display may follow blood glucose with a delay. Pressure on the sensor, a newly inserted sensor, hydration and short data gaps can add uncertainty. When a reading does not match symptoms or the situation, a confirmatory measurement may be appropriate depending on the clinical significance.
Technical context: Blood sugar after eating
Post-meal readings are timed from the start of the meal. Guidelines provide typical targets for many adults with diabetes, but these need individualisation; they are not diagnostic cut-offs for every person and do not replace a personal care plan. Height is only one part of the pattern. Starting value, rise from baseline, time to maximum, duration above the personal range and return are more informative together than one screenshot.
Article-specific interpretation
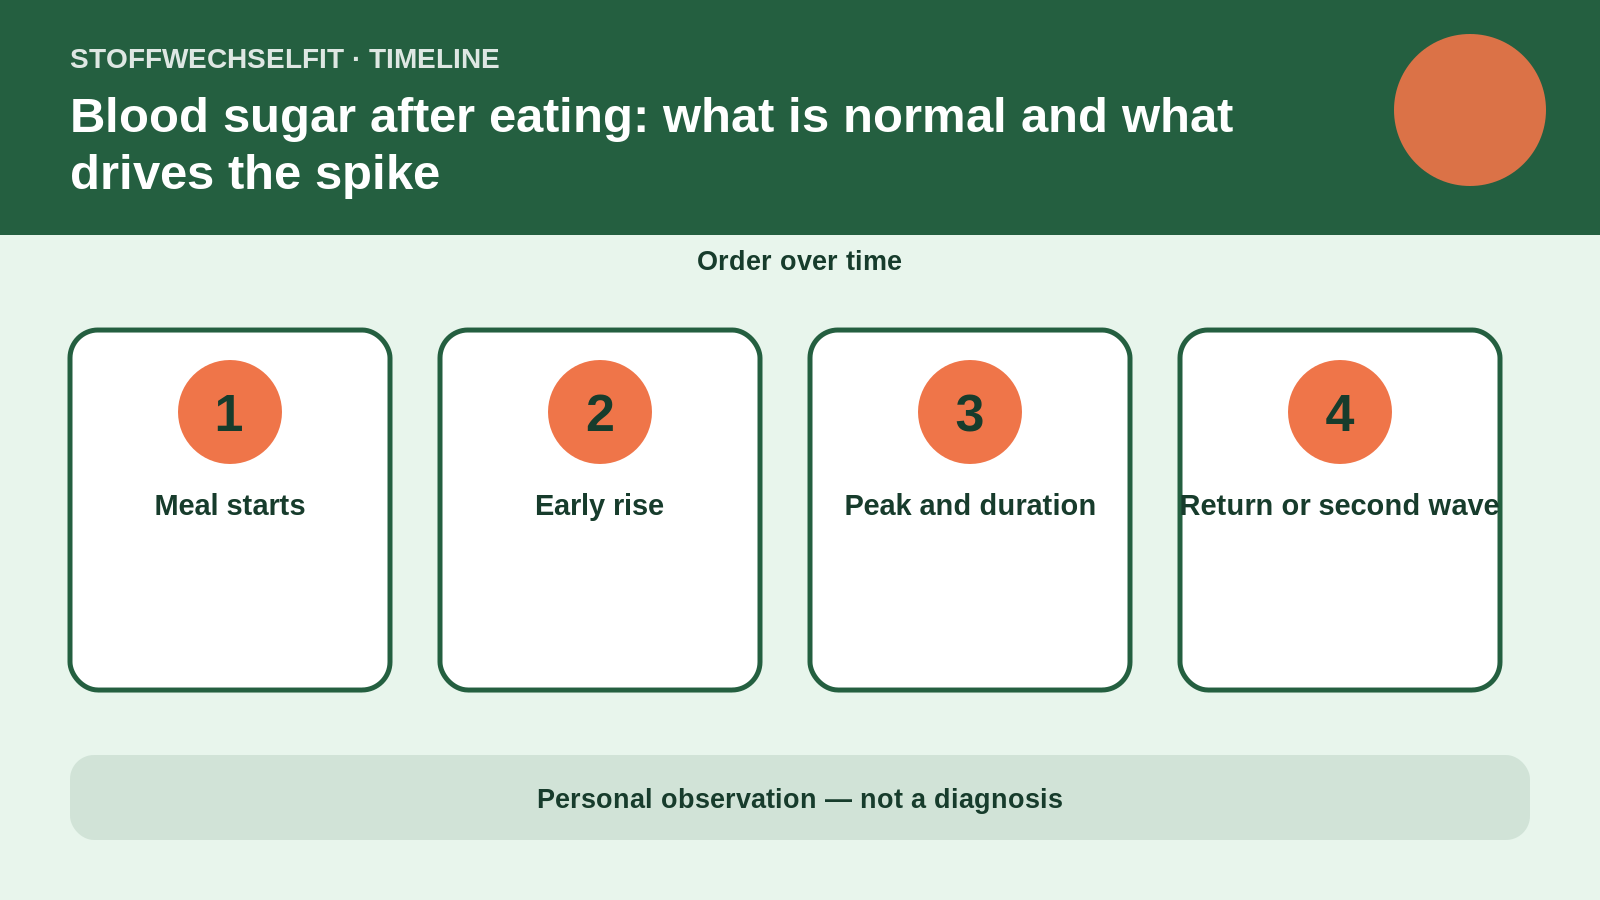
For “Blood sugar after eating: what is normal and what drives the spike”, this means first establishing which of the four phases — Meal starts, Early rise, Peak and duration, Return or second wave — are actually documented. A missing phase is not guessed from the curve. This matters especially because how starting value, timing, height, duration and return of a post-meal curve are evaluated together. More decimal places do not improve research; more complete context does.
Alternative explanations
The competing influences considered are Carbohydrate amount, Meal structure, Starting value and time, Movement and treatment. Several can act at once and partly mask one another. No factor is therefore declared causal merely because it occurred close in time. A plausible explanation remains labelled as plausible until a targeted comparison supports it.
Data sheet and provenance
The data sheet for “Blood sugar after eating: what is normal and what drives the spike” records more than the start and peak. It also covers Meal starts, Early rise, Peak and duration and Return or second wave. Each section states whether a value was measured directly, read from a screenshot, calculated from raw data or reconstructed from memory. This keeps strong research separate from details that require later verification.
Typical failure modes
Common failure modes in this topic are incomplete portions, an incorrect time origin, events added retrospectively and observation ending too soon. For “Blood sugar after eating: what is normal and what drives the spike”, Carbohydrate amount and Starting value and time are particularly important competing explanations. A finding is therefore given more weight only when the same direction appears on several sufficiently similar days and counterexamples are documented as well.
Editorial decision
The editorial decision is to keep the personal experience visible without turning it into universal advice. Headline, hero image, alternative text, captions and conclusion must communicate the same uncertainty. When the article contains an open question, it ends with the next testable step — Set the correct time origin — rather than a claim of effect.
Interpretation matrix
The interpretation matrix for “Blood sugar after eating: what is normal and what drives the spike” assigns every core statement to one of four classes: directly measured, calculated from several readings, physiologically plausible or still open. Direct measurement does not automatically establish causation. A calculated result requires a documented formula and time window. Plausible means consistent with physiology and timing but not isolated in the personal data. Open means that data, repetitions or comparison conditions are missing.
Publication review
Before publication, a final review asks whether the hero image matches the actual message of “Blood sugar after eating: what is normal and what drives the spike”, whether every number can be found in the text, whether units and timing are correct, and whether every image has alternative text and a caption. It also checks that Carbohydrate amount or Meal structure has not accidentally been turned into a proven cause. Only then is the article editorially complete.
Reproducible follow-up plan
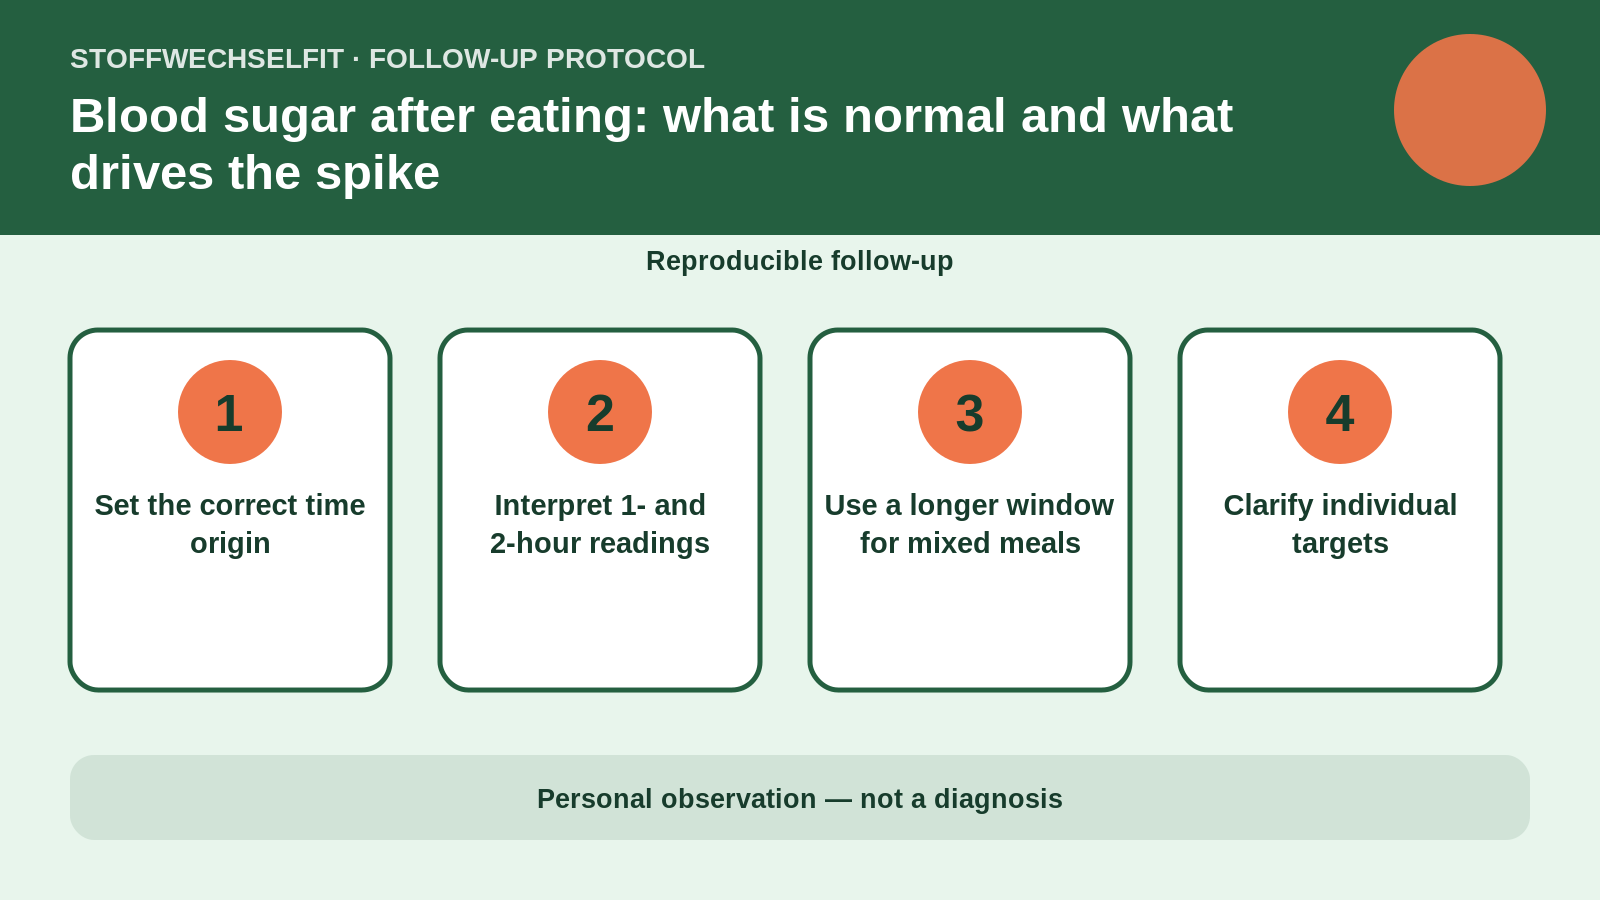
The next useful comparison follows four steps: Set the correct time origin, Interpret 1- and 2-hour readings, Use a longer window for mixed meals, Clarify individual targets. This sequence turns a spontaneous observation into a protocol and reduces the risk of selecting only spectacular days while forgetting ordinary patterns.
What can be transferred
The transferable lesson from “Blood sugar after eating: what is normal and what drives the spike” is therefore not necessarily the exact number. What transfers are the question, the documented conditions and the handling of uncertainty. Other people may respond very differently because of treatment, fitness, insulin sensitivity, digestion or comorbidity.
Comparison rather than snapshot
A credible comparison starts with one clear question and conditions that are as similar as possible. Starting value, trend, time, portion, drinks, activity, sleep, stress and medication all belong in the record. Not every factor can be controlled; the important point is to show differences rather than explain them away afterwards.
State the observation window
Thirty minutes answers a different question from two, four or twelve hours. The article therefore states when observation begins and recognises that mixed meals, alcohol or intense activity can act later. A peak is not interpreted without the pattern before and after it.
Personal readings are not universal limits
Typical guideline targets can provide orientation but require individualisation. Age, comorbidities, pregnancy, medication, hypoglycaemia risk and personal treatment goals change the interpretation. The self-observations shown here do not replace diagnosis or treatment decisions.
Practical safety framework
Marked symptoms, recurrent hypoglycaemia, very high readings, ketones or a pattern that does not fit the situation require clinical assessment rather than another self-experiment. People using insulin or glucose-lowering medication must not derive dose changes or corrections from a blog post.
Further technical limitations
Meals rich in fat or protein may delay the response. A one-hour reading can show an early phase, while a two-hour reading shows another. Mixed meals may require a longer observation window. Symptoms, repeatedly unusual readings or treatment questions require clinical assessment. A blog can explain how to read data, but it cannot set an individual target.
Questions before drawing a conclusion
- Is the starting value for “Blood sugar after eating: what is normal and what drives the spike” documented with trend and time?
- Are Carbohydrate amount and Meal structure described adequately?
- Did observation continue through “Return or second wave”?
- Is there a comparison day after “Set the correct time origin”?
- Is each statement clearly labelled as personal, plausible or generally established?
Sources and context
- American Diabetes Association: Standards of Care in Diabetes—2026, health behaviours and exercise
- American Diabetes Association: Standards of Care in Diabetes—2026, glycaemic goals
- American Diabetes Association: Standards of Care in Diabetes—2026, diabetes technology
- NIDDK: Healthy Living with Diabetes
- WHO: Healthy diet
Medical notice: This article explains a personal observation and general context. It does not replace diagnosis, treatment adjustment or emergency care.
Article ID: SWF-W-006Please quote this ID for corrections or additions.
Sources
Sources as of: 21 Jul 2026.
- Postprandial glucose: healthy usually returns below ~140 mg/dl within ~2 hours; carbohydrate amount is the main driver. Overview. ncbi.nlm.nih.gov (opens in a new window)
- ADA general postprandial target < 180 mg/dl (1–2 h after meal start). Standards of Care. diabetes.org (opens in a new window)
- Frequent postprandial spikes as an independent cardiovascular risk factor; oxidative stress. Review. ncbi.nlm.nih.gov (opens in a new window)